Pharmaceutical translation is commonly described through development stages, publications, patents, candidate progression, or clinical milestones, yet these markers do not establish whether an originating laboratory claim has become reproducible, biologically relevant, manufacturable, pharmacologically credible, or meaningful for patients. This article develops an original Pharmaceutical Translation Observatory as a non-empirical evidence architecture for tracking these distinct transitions without collapsing them into a single maturity score. The proposed observatory separates claims, technologies, products, and evidence packages as related but non-equivalent units of analysis. It connects these units to versioned provenance, independent confirmation, biological and mechanistic relevance, manufacturing and quality readiness, safety and pharmacology, and patient relevance. Evidence-transition indicators are proposed to identify unresolved dependencies, domain discordance, prolonged evidentiary states, reversals, and other potential forms of translational stalling. Governance requirements include interoperable data standards, transparent classification rules, correction and challenge procedures, access controls, durable provenance, and explicit responsibility for interpretation. The architecture is intended to improve the observability of translation rather than predict development success or authorize progression. Its original contribution is a claim-to-patient evidence structure that preserves distinctions between reproducibility and external validity, platform capability and product readiness, model output and pharmaceutical consequence, and scientific plausibility and decision readiness. Validation would require retrospective construct assessment, reproducibility of classification, prospective testing against independently defined transitions, external evaluation across organizations and therapeutic modalities, and investigation of missing evidence, gaming, burden, and unintended consequences. The observatory therefore remains a proposed scholarly framework rather than a validated clinical, manufacturing, regulatory, or deployment system.
INTRODUCTION
Pharmaceutical development is often narrated as movement from discovery through preclinical evaluation, clinical investigation, and eventual implementation. This sequence is administratively useful but scientifically incomplete because it treats development stages as proxies for the strength, transportability, and practical relevance of the evidence accumulated within them. Pharmaceutical development combines stage-dependent attrition, interacting causes of failure, and organizational discontinuities between academic discovery and downstream development [1-3]. A candidate may therefore advance administratively while retaining unresolved weaknesses in replication, mechanism, manufacturing, exposure, safety, or patient relevance.
Stage-transition statistics can describe where programs discontinue, but they do not reveal whether the originating claims were independently reproduced, whether relevant biological systems were represented, or whether the product and process remained compatible as development requirements changed [1]. Similarly, movement from an academic laboratory into an industrial development environment may alter ownership, methods, materials, objectives, and evidentiary standards, making continuity difficult to infer from publication or licensing records alone [3]. Translation should consequently be examined as a sequence of evidentiary transformations rather than as the mere survival of a project through predefined organizational gates.
This article proposes the Pharmaceutical Translation Observatory as an original Evidence-Observatory Architecture. The observatory is defined as a versioned system for linking identifiable claims, technologies, products, and evidence packages to distinct domains of readiness, uncertainty, confirmation, and decision use. Its purpose is not to replace development governance or establish another universal readiness scale. It is intended to make visible which evidence exists, which unit it concerns, how it has changed, what dependencies remain unresolved, and which inferences cannot yet be justified.
The central contribution is a non-compensatory architecture in which strong evidence in one domain cannot automatically erase weakness in another. Reproducibility does not establish human relevance; mechanistic plausibility does not establish product feasibility; manufacturing capability does not establish clinical value; and predictive model output does not constitute a pharmaceutical, regulatory, or patient-level consequence. These relationships are presented as an original conceptual synthesis requiring empirical validation rather than as an established prediction system, clinical recommendation, or regulator-endorsed framework.
Why translational progress is poorly measured
Translational progress is poorly measured partly because evidence generation is frequently represented through visible outputs rather than through the conditions that make those outputs credible and transferable. Publications, positive experiments, candidate nominations, patents, and milestone completion can document activity while concealing weaknesses in design, reporting, incentives, materials, analysis, and transparency. Reproducibility is therefore better understood as a property of an interdependent research system than as the isolated repetition of a result [4]. The observatory interprets this established insight as a requirement to record how evidence was produced, qualified, challenged, and revised.
A second difficulty is that published claims may not contain sufficient information for faithful examination outside the originating setting. Missing protocols, unavailable materials, analytical ambiguity, incomplete original records, and differences between planned and executable methods can obstruct replication before biological disagreement is even assessed [5]. Such conditions create an observability problem: failure to reproduce may reflect an incorrect claim, an inadequately specified claim, contextual dependence, or an inability to reconstruct the original evidentiary conditions. The proposed observatory would preserve these explanations separately rather than assigning all unsuccessful attempts to one undifferentiated failure category.
Structured reporting can improve this observability by connecting claims to their materials, design choices, analytical procedures, and reporting context [6]. These descriptors would allow an evidence package to be inspected, compared, versioned, and transferred more reliably across teams and development stages. However, reporting completeness is not equivalent to experimental validity. A fully documented experiment may remain biased, biologically irrelevant, or non-transferable, whereas incomplete reporting may prevent a potentially valid claim from being evaluated independently.
Poor measurement also arises because translational progress is multidimensional and may be asynchronous. Reproducibility may increase while manufacturability deteriorates; mechanistic understanding may strengthen without identifying a clinically meaningful population; or process control may improve while safety uncertainty remains unresolved. Alternative explanations for apparent stalling must therefore include scientific weakness, insufficient evidence generation, strategic reprioritization, resource constraints, ownership changes, and limitations in what can be observed publicly. The proposed observatory cannot eliminate these ambiguities, but it may distinguish them more clearly than stage labels or output counts alone.
Proposed pharmaceutical translation observatory
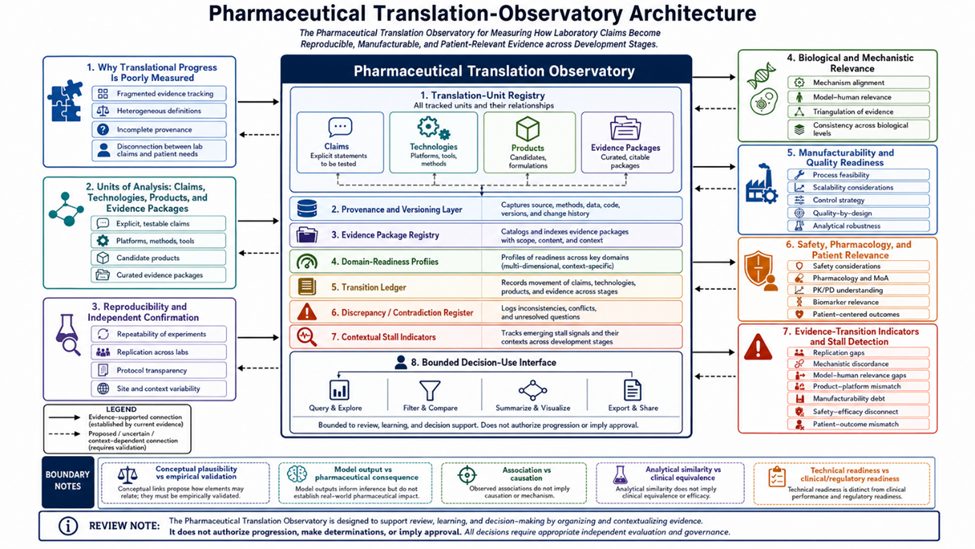
Therapeutic development has previously been represented as a dynamic network of interacting activities, dependencies, and failure-prone transitions rather than as a simple linear pipeline [7]. Building on that principle, the proposed Pharmaceutical Translation Observatory places a translation-unit registry at the center of a layered architecture connecting evidence provenance, readiness domains, discrepancies, transitions, and bounded decision use. Figure 1 presents the original conceptual synthesis for pharmaceutical translation-observatory architecture, showing how the article’s principal components, evidence relationships, uncertainties, and decision boundaries are connected.
|
|
|
Figure 1. Pharmaceutical Translation-Observatory Architecture. |
The figure is an original conceptual synthesis developed for “The Pharmaceutical Translation Observatory for Measuring How Laboratory Claims Become Reproducible, Manufacturable, and Patient-Relevant Evidence across Development Stages.” Arrows and grouping indicate proposed or evidence-supported relationships rather than measured effect sizes. The figure does not represent a validated predictive model, clinical recommendation, regulatory determination, or deployment-ready system.
The observatory’s first layer is a translation-unit registry containing claims, technologies, products, and evidence packages. Each registered unit would carry an identifier, scope, context of use, ownership or custodianship, current version, and links to supporting or conflicting records. A cross-cutting provenance layer would apply pharmaceutical implementations of findability, accessibility, interoperability, and reusability while preserving the distinction between accessible evidence and scientifically valid evidence [8]. Provenance would include source lineage, materials, methods, data transformations, analytical decisions, corrections, and superseded versions.
The second layer is an entity–relationship evidence architecture. Contemporary evidence platforms demonstrate that heterogeneous sources can be organized through explicit entities, typed relationships, provenance, and periodic updating [9]. The proposed observatory extends this logic beyond target–disease evidence to relationships among experimental claims, model systems, technologies, candidate products, manufacturing processes, safety findings, pharmacology models, and patient populations. This extension is conceptual: the suitability of any shared ontology or relationship schema would require testing across therapeutic areas, modalities, institutions, and development stages.
The third layer consists of separate evidence profiles for reproducibility, biological and mechanistic relevance, manufacturing and quality readiness, safety and pharmacology, and patient relevance. These profiles would not be combined automatically into a total readiness score. Instead, each would contain the evidence available, its context, the remaining uncertainty, unresolved dependencies, conflicting findings, and required validation. A translation ledger would then record proposed movement between evidentiary states, including the warrant for the transition and any evidence that challenges or reverses it.
The final layer is a bounded decision-use interface supported by governance, audit, correction, access, and challenge procedures. Its function would be to organize review, expose evidentiary discontinuities, and support accountable questioning. It would not authorize progression, determine regulatory acceptability, predict clinical success, or replace expert judgment. The architecture’s value must therefore be evaluated by whether it improves classification consistency, evidentiary traceability, detection of unresolved dependencies, and decision transparency without generating excessive burden or false confidence.
Units of analysis: claims, technologies, products, and evidence packages
The observatory requires distinct units of analysis because pharmaceutical readiness cannot be inferred reliably from an undifferentiated project label. Multidimensional development frameworks show that target understanding, tissue exposure, safety, patient selection, and other development conditions represent separable forms of evidence [10]. The proposed observatory applies a non-compensatory interpretation: strength in one evidentiary dimension may inform the overall assessment, but it cannot automatically substitute for missing evidence in another. A persuasive mechanism, for example, cannot erase an unresolved manufacturing constraint or an uncertain exposure–response relationship.
A claim is a bounded scientific assertion concerning an observed relationship, mechanism, performance characteristic, or expected consequence. A technology is a method, model, platform, or enabling capability through which claims may be generated or products may be developed. A product is a defined therapeutic candidate with product-specific composition, process, quality, pharmacology, and intended-use characteristics. These units must remain separate because conclusions concerning targets or mechanisms can change substantially when the underlying entities, denominators, development programs, and approval outcomes are defined differently [11]. Evidence supporting a target class or technological platform cannot therefore be transferred automatically to an individual product.
An evidence package is the versioned set of materials, methods, data, analyses, results, uncertainties, provenance records, and contextual information used to evaluate one or more claims. Preclinical assay guidance demonstrates that interpretation depends on assay purpose, controls, performance characteristics, biological context, and the question the assay is intended to address [12]. Within the observatory, the evidence package would consequently be treated as more than a collection of publications. It would record how a claim was operationalized, which observations support or contradict it, which analytical choices were made, and where the evidence is transferable.
The proposed relationships among these units are typed rather than assumed. A claim may be generated through a technology, incorporated into a product rationale, supported by several evidence packages, contradicted by another package, or remain relevant only within a specified context. A product may depend on a platform without inheriting all evidence attributed to that platform. Likewise, a reproducible assay result may support a claim without establishing mechanism, manufacturability, safety, or patient relevance. These distinctions are proposed to reduce unsupported evidentiary transfer, but their practical usefulness and classification reliability require empirical evaluation.
Reproducibility and independent confirmation
Reproducibility should be represented as several related but non-equivalent conditions. Complete reporting, prospective research-quality systems, and multilaboratory confirmation address distinct requirements for reproducible preclinical evidence [13-15]. None independently proves that a claim is biologically correct or therapeutically relevant.
The observatory therefore proposes six descriptive states: insufficiently specified, technically repeated, internally reproduced, independently reproduced, cross-site confirmed, and discrepant or unresolved. These states describe the evidence history rather than a universal hierarchy or automatic progression pathway.
Independent confirmation must preserve differences in materials, operators, laboratories, analytical plans, and experimental context. A finding repeated only under conditions controlled by the originating group remains distinguishable from one reproduced by independent investigators [15].
Disagreement should remain visible rather than being averaged into an apparently stable conclusion. The observatory would record whether divergence reflects unavailable methods, measurement variation, contextual dependence, analytical disagreement, or possible failure of the original claim. These classifications require empirical testing and do not establish causation.
Biological and mechanistic relevance
Reproducibility within a model does not establish relevance beyond that model. External-validity limitations, organs-on-chips, and organoids provide complementary evidence about biological and human relevance, but none is sufficient across every pharmaceutical context [16-18].
The proposed biological-relevance profile would record mechanism alignment, disease representation, species or tissue correspondence, exposure realism, system complexity, and the population represented. Organs-on-chips may address selected physiological interactions but require qualification for defined uses [17].
Organoids may preserve human cellular organization and disease features while remaining limited by maturation, standardization, vascularization, systemic interactions, or incomplete representation of clinical heterogeneity [18]. Their contribution must therefore be attached to a specific claim and question.
Mechanistic coherence, human-derived biology, and independent reproduction may strengthen an evidence package without proving clinical benefit. Table 1 organizes the evidence, constructs, relationships, uncertainties, and boundary conditions required for definitions, components, relationships, and intended uses in the pharmaceutical translation observatory for measuring how laboratory claims become.
Table 1. Definitions, components, relationships, and intended uses in The Pharmaceutical Translation Observatory for Measuring How Laboratory Claims Become.
|
Component or scientific dimension |
Problem addressed |
Inputs or determinants |
Proposed mechanism or relationship |
Expected contribution |
Evidence required |
Failure or uncertainty risk |
Boundary statement |
|
Laboratory claim |
Claims are treated as self-contained facts |
Assay purpose, controls, observations, analysis, context [12]. |
Proposed: register each bounded assertion separately |
Traceable claim evaluation |
Reconstructable methods and supporting data |
Ambiguous scope or selective reporting |
A registered claim is not a validated claim |
|
Technology or platform |
Platform capability is transferred automatically to products |
Technical function, operating conditions, qualification evidence [17]. |
Proposed: link platform evidence to products through explicit relationships |
Reduced unsupported transfer |
Context-specific performance evidence |
Platform–product mismatch |
Technical capability does not establish product readiness |
|
Product |
Project labels conceal product-specific evidence |
Composition, process, quality, pharmacology, intended use [10]. |
Proposed: maintain a separate product-readiness profile |
Product-specific interpretation |
Integrated product and process evidence |
Evidence borrowed from targets or platforms |
Product progression is not proof of patient relevance |
|
Evidence package |
Publications omit evidence lineage |
Materials, methods, data, analysis, uncertainty, provenance [6]. |
Proposed: create versioned evidence bundles |
Auditability and comparison |
Accessible records and documented transformations |
Missing or superseded evidence |
Documentation does not establish validity |
|
Independent confirmation |
Internal repetition is mistaken for external reproduction |
Site, operator, material, protocol, and analysis differences [15]. |
Proposed: classify confirmation by independence and context |
Improved transportability assessment |
Independent replication or multilaboratory evidence |
Shared bias or inaccessible methods |
Replication does not establish mechanism |
|
Biological relevance |
Reproducible model effects may not represent human disease |
Species, tissue, mechanism, exposure, disease context [16]. |
Proposed: maintain a context-specific relevance profile |
Clearer interpretation of model evidence |
Orthogonal and human-relevant evidence |
Model incompleteness or context dependence |
Human-derived evidence is not automatically clinically predictive |
|
Domain-readiness profile |
Evidence is collapsed into one score |
Reproducibility, relevance, manufacturing, safety, pharmacology, patient evidence |
Proposed: preserve non-compensatory domains |
Visibility of discordance |
Domain-specific evidence and uncertainty |
False reassurance from aggregation |
One strong domain cannot erase another’s deficiency |
|
Transition record |
Stage changes lack evidentiary justification |
Source state, destination state, evidence warrant, date, dependency [7]. |
Proposed: record every claimed evidence transition |
Transparent progression history |
Versioned and reviewable justification |
Administrative milestones mistaken for evidence |
A recorded transition does not authorize progression |
Manufacturability and quality readiness
Manufacturability is not a late operational detail. Product and process understanding, quality attributes, control strategies, monitoring, and lifecycle change management are central to pharmaceutical manufacturing readiness [19].
Laboratory production demonstrates feasibility only under specified conditions. Integrated manufacture additionally depends on material variability, unit-operation interactions, process continuity, scale, control, and consistent dosage-form quality [20].
Platform capability must also remain distinct from product-specific readiness. On-demand production can demonstrate important technical and quality capabilities, but each product still requires evidence concerning identity, purity, potency, consistency, stability, and intended use [21].
The observatory proposes a manufacturing profile covering material availability, process definition, critical quality attributes, analytical capability, control strategy, scale dependence, site transfer, stability, and change sensitivity. These dimensions would remain descriptive until validated for particular modalities.
Manufacturing evidence may expose incompatibilities that biological evidence cannot resolve. Conversely, a controllable process cannot establish therapeutic benefit. The observatory would therefore show manufacturing readiness alongside—not beneath or after—mechanistic, safety, pharmacological, and patient-relevance evidence.
Safety, pharmacology, and patient relevance
Safety evidence must be interpreted within a defined context of use. Predictive models require mechanistic rationale, qualification, performance assessment, and clarity regarding the decisions they are intended to inform [22].
Human-relevant systems can strengthen safety evaluation when performance is compared with independent outcomes and when limitations remain visible [23]. A favorable result from one platform cannot be generalized automatically across toxicities, compounds, populations, or development settings.
Pharmacology models become decision-relevant only when their purpose, assumptions, data, uncertainty, verification, and intended application are explicit [24]. Model output must remain distinguishable from observed exposure, clinical response, treatment recommendation, or regulatory consequence.
Patient relevance requires correspondence among population, disease state, exposure, comparator, endpoint, treatment setting, and meaningful outcome. Table 2 organizes the evidence, constructs, relationships, uncertainties, and boundary conditions required for testable propositions, evidence requirements, and validation criteria for the pharmaceutical translation observatory for measuring how laboratory claims become..
Table 2. Testable propositions, evidence requirements, and validation criteria for The Pharmaceutical Translation Observatory for Measuring How Laboratory Claims Become.
|
Architecture layer or process stage |
Core function |
Information or material flow |
Interaction with other components |
Validation criterion |
Potential failure mode |
Human or experimental responsibility |
Readiness boundary |
|
Unit registry |
Separate claims, technologies, products, and packages |
Identifiers, definitions, versions, relationships |
Feeds all evidence profiles |
Independent classifiers distinguish units consistently |
Entity conflation |
Domain experts resolve ambiguous identity |
Classification does not establish readiness |
|
Provenance layer |
Preserve evidence lineage |
Materials, methods, data, transformations, corrections |
Supports audit and replication |
Records are reconstructable across organizations |
Missing or selective provenance |
Data stewards and investigators maintain lineage |
Provenance does not establish validity |
|
Reproducibility profile |
Record repetition and confirmation |
Protocols, sites, operators, outcomes |
Informs relevance and discrepancy records |
Classification agrees with independent replication history |
Shared bias or inaccessible methods |
Independent laboratories test claims |
Reproduction does not establish clinical value |
|
Biological-relevance profile |
Evaluate model–question correspondence |
Mechanism, tissue, species, exposure, disease state |
Connects claims to safety and pharmacology |
Ratings correspond with prespecified external evidence |
Model overinterpretation |
Experimental scientists justify context of use |
Plausibility is not patient relevance |
|
Manufacturing profile |
Expose product–process constraints |
Materials, process parameters, quality evidence |
Interacts with product and platform records |
Profile predicts independently observed process challenges |
Modality-specific misclassification |
Manufacturing and quality specialists review evidence |
Feasibility is not validated manufacture |
|
Safety and pharmacology profile |
Qualify predictive and mechanistic evidence |
Exposure, response, toxicity, uncertainty, model assumptions |
Connects product evidence to intended population |
Conclusions reproduce under external evaluation |
Model transport failure |
Pharmacologists and safety experts define use boundaries |
Model output is not a treatment decision |
|
Patient-relevance profile |
Link evidence to populations and outcomes |
Population, disease state, endpoint, comparator, setting |
Depends on all upstream domains |
Classifications align with independently defined clinical relevance |
Surrogate or population mismatch |
Clinicians and patient experts assess meaning |
Relevance does not establish net benefit |
|
Transition and stall layer |
Detect unresolved dependencies and discordance |
State changes, dwell time, reversals, evidence gaps |
Draws from every profile |
Prospective signals distinguish actionable gaps without excessive false alerts |
Gaming or arbitrary thresholds |
Accountable reviewers interpret signals |
A stall flag is not an automatic stop rule |
Evidence-transition indicators and stall detection
Development transition rates vary by therapeutic area and context, making universal benchmarks potentially misleading [25]. The observatory would therefore compare evidence transitions within relevant modality, disease, organizational, and development contexts.
Differences between available scientific knowledge and active pharmaceutical development can be mapped as evidence-coverage gaps [26]. Such gaps may reflect neglected opportunities, weak evidence, strategic constraints, or practical barriers rather than a single cause.
Proposed stall indicators include prolonged unresolved states, absence of independent confirmation, domain discordance, unclear context of use, manufacturability debt, safety–efficacy disconnect, provenance discontinuity, and repeated reversal of a claim or product rationale.
These indicators would identify conditions for investigation, not validated probabilities of failure. Calibration requires longitudinal evidence, prespecified outcomes, assessment of false alerts, and evaluation of whether users respond by improving evidence or merely optimizing documentation.
Governance, data standards, and transparency
Technical accessibility alone is insufficient for responsible evidence stewardship. FAIR implementation requires attention to governance, responsibility, interpretation, access, and the conditions under which evidence may be reused [27].
Durable repositories also require transparency, responsibility, user focus, sustainability, and appropriate technology [28]. The observatory would apply these principles to version histories, correction records, access controls, retention, and challenge procedures.
A minimum common data model should define translation units, evidence relationships, contexts of use, uncertainty descriptors, confirmation states, and reasons for transition. Local extensions would remain necessary because evidence structures differ across modalities and organizations.
Transparency cannot convert biased or irrelevant evidence into reliable knowledge. Governance should instead make limitations visible, assign responsibility for classifications, preserve dissent, and permit correction without implying that the observatory itself determines scientific truth.
Limitations and implementation priorities
Computational integration may amplify problems in data quality, transferability, interpretability, validation, and hidden bias [29]. Automated classification should therefore remain reviewable and should not replace scientific or contextual judgment.
Autonomous experimentation may accelerate hypothesis selection and experiment generation, but experimental speed does not establish reproducibility, manufacturability, safety, or patient relevance [30]. The origin of evidence should be recorded without granting automated evidence preferential status.
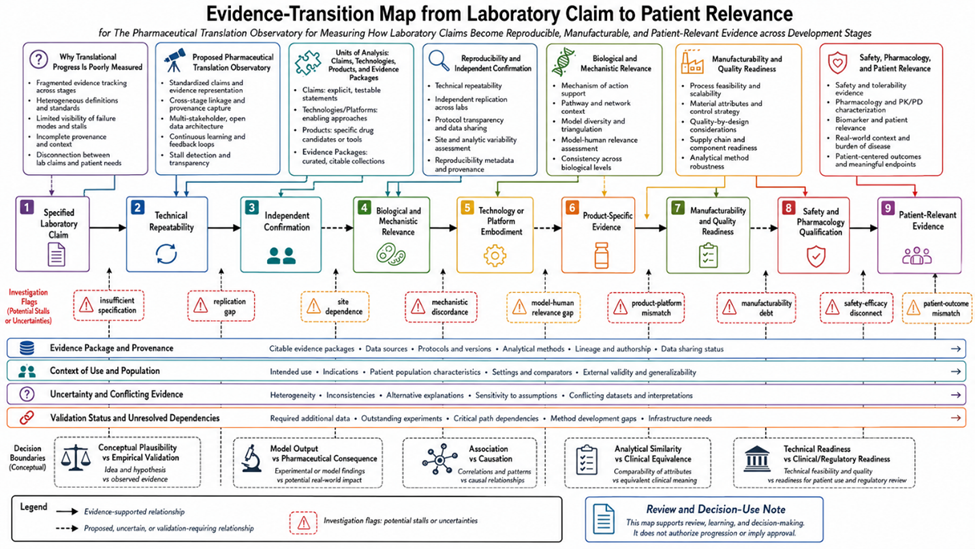
Figure 2 presents the original conceptual synthesis for evidence-transition map from laboratory claim to patient relevance, showing how the article’s principal components, evidence relationships, uncertainties, and decision boundaries are connected.
|
|
|
Figure 2. Evidence-Transition Map from Laboratory Claim to Patient Relevance. |
The figure is an original conceptual synthesis developed for “The Pharmaceutical Translation Observatory for Measuring How Laboratory Claims Become Reproducible, Manufacturable, and Patient-Relevant Evidence across Development Stages.” Arrows and grouping indicate proposed or evidence-supported relationships rather than measured effect sizes. The figure does not represent a validated predictive model, clinical recommendation, regulatory determination, or deployment-ready system.
Initial implementation should focus on a minimum common model, retrospective feasibility testing, inter-rater classification, prospective evaluation, and cross-organizational pilots. Further priorities include detecting missing evidence, selective disclosure, indicator gaming, administrative burden, modality dependence, and unintended effects on scientific behavior.
CONCLUSION
The Pharmaceutical Translation Observatory is proposed as an original architecture for tracing how bounded laboratory claims become—or fail to become—reproducible, biologically relevant, manufacturable, pharmacologically credible, and patient-relevant evidence. Its central contribution is the separation of claims, technologies, products, and evidence packages within versioned, non-compensatory evidence profiles and explicit transition records. The observatory may improve evidentiary visibility and accountability, but it cannot establish causation, predict development success, authorize progression, substitute for expert judgment, or confer clinical or regulatory readiness. Its constructs, classifications, transition indicators, governance effects, and decision utility require independent empirical validation across contexts.
ACKNOWLEDGMENTS: None
CONFLICT OF INTEREST: None
FINANCIAL SUPPORT: None
ETHICS STATEMENT: None

 IJPRAS